



Advancing Integrative Health in the Era of Precision and Digital Care
[Year:2026] [Month:January-June] [Volume:3] [Number:1] [Pages:3] [Pages No:i - iii]
DOI: 10.5005/jihr-3-1-iv | Open Access | How to cite |
Abstract
Health systems worldwide face rising chronic disease burden, increasing multimorbidity, and growing expectations for care that is both effective and experience-centered. So, it is necessary to align biomedical knowledge with patient values and practical care delivery by converging evidence-focused traditional and complementary approaches, precision and multi-omics medicine, and the digital transformation of data capture and clinical decision-making. Traditional medicine and integrative care contribute therapeutic concepts, diagnostic frameworks, and whole-person outcomes orientations, yet the field must close persistent gaps in evidence generation, standardization, regulatory pathways, and equitable access. Precision medicine reframes one-size-fits-all care into risk stratification and tailored therapeutics, but its translational pipeline remains incomplete and unevenly implemented, with well-documented diversity and equity deficits. Digital innovation can unify these aims through continuous measurement, real-world evaluation, and adaptive feedback loops, while requiring careful governance to mitigate algorithmic bias, privacy risks, and digital divides.
This editorial advances a convergent research agenda centered on mechanism-informed biomarker discovery from traditional systems, multimodal phenotyping with digital biomarkers and patient-reported outcomes, and rigorous real-world evidence designs with precision-informed stratification. By integrating governance and equity criteria from the outset, future healthcare can become simultaneously scientifically rigorous, culturally responsive, and broadly accessible.

Ebola Virus Disease: What We Know, How Deadly It is, and How It Spreads Compared to COVID-19?
[Year:2026] [Month:January-June] [Volume:3] [Number:1] [Pages:4] [Pages No:1 - 4]
Keywords: Bodily fluid transmission, Contact tracing, Filoviridae, Monoclonal antibody therapy, Outbreak containment, Zoonotic spillover
DOI: 10.5005/jihr-11055-0035 | Open Access | How to cite |
Abstract
Ebola virus disease (EVD) remains one of the most lethal infectious diseases known to medicine, with an average case fatality rate (CFR) of approximately 50% and historical outbreak CFRs ranging from 25% to 90%, depending on virus species and health care context. Caused exclusively by Ebola virus (Orthoebolavirus zairense) within the family Filoviridae, EVD has been recognized since its first identification in the Democratic Republic of the Congo in 1976, with at least 34 outbreaks documented since then and evidence of increasing frequency after 1994. Meta-analyses of global outbreak data report pooled CFRs of approximately 60–65%, with Zaire ebolavirus consistently associated with the highest fatality among the species that infect humans. Ebola virus disease is transmitted through close, direct physical contact with the blood, body fluids, or contaminated materials of symptomatic individuals or deceased persons; it is not an airborne infection. This fundamental distinction in transmission mode explains why EVD does not spread like COVID-19. While SARS-CoV-2 propagates via respiratory aerosols across distances in everyday settings, Ebola is constrained to contact-based routes, resulting in more limited but concentrated outbreak dynamics, with estimated basic reproduction numbers of 1.5–2.5 during the 2014 West Africa epidemic. Critically, EVD is not infectious before symptom onset, enabling a response architecture centered on rapid case identification, isolation, rigorous infection prevention and control, safe burial practices, and intensive contact tracing. Significant therapeutic advances have strengthened outbreak response. Two WHO-prequalified vaccines–Ervebo and the Zabdeno/Mvabea regimen—and two strongly recommended monoclonal antibody treatments, mAb114 (Ansuvimab) and REGN-EB3 (Inmazeb), are now available for EBOV outbreaks. Preparedness planning must account for recurrent zoonotic spillover risk, survivor persistence of virus in immune-privileged sites, and ongoing gaps in diagnostic and response capacity in endemic regions.

Study of Immunological Markers in Clinically Suspected Cases of Dengue
[Year:2026] [Month:January-June] [Volume:3] [Number:1] [Pages:4] [Pages No:5 - 8]
Keywords: Dengue, IgG, IgM, NS1 antigen, Retrospective, Serological markers, Serology
DOI: 10.5005/jihr-11055-0034 | Open Access | How to cite |
Abstract
Dengue virus is transmitted by mosquitoes and represents a major public health problem in tropical and subtropical regions of the world. Early diagnosis is essential for appropriate patient management and prevention of complications. Aim of the study: The main objective was to assess the distribution of dengue immunological markers [NS1 antigen, immunoglobulin M (IgM) antibody, and immunoglobulin G (IgG) antibody] among clinically suspected dengue patients and to correlate these findings with thrombocytopenia. Materials and methods: The present study was a retrospective descriptive study that involved 352 serum samples from clinically suspected dengue patients. NS1 antigen and antibody (IgM, IgG) levels were measured using an immunochromatography (ICT) test for NS1. Results: Out of 352 samples, 109 (30.96%) were seropositive for at least one dengue serological marker. NS1 antigen was detected in 42 (38.53%) cases, IgM antibody in 28 (25.68%) cases, and IgG antibody in 9 (8.25%) cases. Multiple-marker positivity was observed in 30 (27.54%) cases, including combinations of NS1 + IgM, IgM + IgG, and NS1 + IgM + IgG. Thrombocytopenia was the most prominent hematological finding and was observed more frequently among seropositive patients than seronegative patients. Conclusion: NS1 antigen, IgM, and IgG antibodies are important markers for the laboratory diagnosis of dengue infection. NS1 antigen helps with early detection during the acute phase, while IgM indicates recent infection and IgG suggests past exposure. The combined use of these markers improves diagnostic accuracy and helps determine the stage of disease.
[Year:2026] [Month:January-June] [Volume:3] [Number:1] [Pages:8] [Pages No:9 - 16]
Keywords: Anti-inflammatory agents, Facial edema, Maxillofacial surgery, Oral surgical procedures, Postoperative complications
DOI: 10.5005/jihr-11055-0026 | Open Access | How to cite |
Abstract
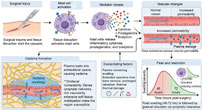
Background: Postoperative swelling is an inevitable inflammatory response following oral and maxillofacial surgery (OMFS). However, excessive edema can restrict mandibular movement, hinder functional recovery, complicate airway assessment, and increase patient discomfort. Achieving predictable surgical outcomes relies on effectively modulating this inflammatory response. Aim: This educational review aims to evaluate both novel and established methods for reducing postoperative swelling and to examine their clinical applicability in modern oral and maxillofacial practice. Methodology: A structured narrative review was performed using PubMed, Scopus, and Google Scholar, covering literature from January 2000 to August 2025. Relevant clinical studies were identified, screened, and qualitatively synthesized based on methodological quality and clinical relevance. Conclusion: Current evidence supports a personalized, multimodal approach that integrates targeted pharmacological interventions, refined surgical techniques, adjunctive physical therapies, and objective postoperative monitoring. However, the establishment of definitive standardized protocols is limited by inconsistent study designs and outcome reporting. To develop reproducible, evidence-based practices that optimize recovery and enhance patient-centered care in contemporary OMFS, high-quality comparative research is essential.
Orthodontics at the Nanoscale—Redefining Treatment through Nanotechnology: A Narrative Review
[Year:2026] [Month:January-June] [Volume:3] [Number:1] [Pages:7] [Pages No:17 - 23]
Keywords: Adhesive restorations, Aligner therapy, Artificial intelligence, Health technology, Orthodontics
DOI: 10.5005/jihr-11055-0028 | Open Access | How to cite |
Abstract
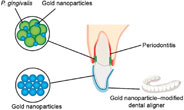
Traditional orthodontic materials, while integral to clinical practice, face inherent limitations such as frictional resistance, corrosion, and susceptibility to plaque accumulation. Nanotechnology has emerged as a promising field to address these challenges by manipulating materials at the nanoscale to enhance mechanical, chemical, and biological properties. This narrative review synthesizes predominantly preclinical evidence on nanomaterials in orthodontic therapy, spanning archwires, brackets, adhesives, and auxiliaries. Nanocoatings and nanofillers—including titanium dioxide (TiO2), silver nanoparticles (AgNPs), and graphene—have shown promising results in preclinical studies for reducing friction, improving bond strength, and inhibiting biofilm formation to prevent white spot lesions. The review further explores nanotechnology in clear aligners and temporary anchorage devices (TADs), highlighting improvements in mechanical stability and osseointegration. Future applications, such as shape memory polymers (SMPs), smart brackets with nanosensors, and nanorobotics, theoretically offer precise force control and real-time monitoring. Despite these encouraging developments, concerns regarding nanoparticle toxicity and long-term biocompatibility necessitate further rigorous clinical evaluation. The current evidence base is predominantly in vitro and animal-derived; robust clinical trials are needed before nanotechnology can be widely translated into routine orthodontic practice.
Limitations and Pitfalls of Artificial Intelligence in Orthodontics: A Narrative Review
[Year:2026] [Month:January-June] [Volume:3] [Number:1] [Pages:7] [Pages No:24 - 30]
Keywords: Artificial intelligence, Cephalometric analysis, Deep learning, Limitations, Machine learning, Narrative review, Orthodontics
DOI: 10.5005/jihr-11055-0029 | Open Access | How to cite |
Abstract
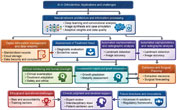
Artificial intelligence (AI) is increasingly integrated into orthodontics, supporting tasks ranging from cephalometric landmark detection to treatment planning and remote monitoring. Evidence from recent literature shows consistent progress in diagnostic accuracy and workflow efficiency; however, its clinical impact remains dependent on validation, dataset quality, and regulatory clearance. Current applications demonstrate benefits in automated image analysis, multimodal data interpretation, and decision-support systems, yet real-world limitations persist. A major concern is restricted generalizability, as most models are trained on unicentric or homogeneous datasets, which raises risks of algorithmic bias and reduced reliability in complex or diverse clinical scenarios. Furthermore, ethical and legal factors, such as accountability, data privacy, and lack of standardized evaluation protocols, continue to limit large-scale adoption. Only a small proportion of AI tools have reached regulatory approval, underscoring the gap between experimental success and clinical maturity. This review synthesizes existing evidence, outlines key challenges, and highlights future directions, emphasizing the need for multicenter datasets, explainable AI systems, and structured regulatory frameworks to ensure safe and effective implementation in orthodontic practice.

Digital Orthodontic Workflow: A Narrative Review
[Year:2026] [Month:January-June] [Volume:3] [Number:1] [Pages:7] [Pages No:31 - 37]
Keywords: Artificial intelligence, Clear aligners, Computer-aided design/computer-aided manufacturing, Digital orthodontics, Digital workflow, Intraoral scanning, Three-dimensional printing
DOI: 10.5005/jihr-11055-0031 | Open Access | How to cite |
Abstract
Background: The integration of digital technologies has fundamentally transformed contemporary orthodontic practice. Conventional workflows based on physical impressions, plaster models, and manual appliance fabrication are increasingly being replaced by digitally driven processes. The digital orthodontic workflow encompasses intraoral scanning, digital diagnosis and virtual treatment planning, computer-aided design and manufacturing (CAD/CAM), three-dimensional (3D) printing, and digitally guided clinical delivery. Objective: To provide a comprehensive narrative overview of the digital orthodontic workflow, focusing on its key components, clinical applications, accuracy, advantages, limitations, and emerging trends based on current evidence. Materials and methods: A nonsystematic narrative review was conducted in accordance with the Scale for the Assessment of Narrative Review Articles framework. Electronic databases, including PubMed/MEDLINE, Scopus, Web of Science, and Google Scholar, were searched for peer-reviewed articles published between January 2000 and December 2023. Systematic reviews, clinical studies, validation studies, and relevant narrative reviews addressing components of the digital orthodontic workflow were qualitatively analyzed. Results: Evidence from multiple systematic reviews and clinical studies demonstrates that digital study models and intraoral scans provide clinically acceptable accuracy and reliability comparable to conventional methods. Digital diagnosis and virtual treatment planning enhance three-dimensional visualization, treatment predictability, and patient communication. CAD/CAM technologies and 3D printing enable the fabrication of customized orthodontic appliances with high dimensional accuracy. Clear aligner therapy represents a fully digital treatment modality, showing effectiveness for mild to moderate malocclusions, although limitations remain for complex tooth movements. Emerging advancements, including in-office 3D printing, digital monitoring, and artificial intelligence applications, further expand the scope of digital orthodontics. Conclusion: The current body of literature supports the digital orthodontic workflow as an accurate, efficient, and patient-centered approach to orthodontic care. While digital technologies offer significant advantages, the overall strength of evidence remains moderate. Optimal clinical outcomes continue to depend on clinician expertise, sound biomechanical principles, and appropriate case selection. Further well-designed randomized clinical trials and long-term studies are required to strengthen the evidence base.
[Year:2026] [Month:January-June] [Volume:3] [Number:1] [Pages:7] [Pages No:38 - 44]
Keywords: Arteriovenous malformations, Bleomycin, Ethanol, Head and neck vascular malformations, Sclerotherapy, Vascular malformations
DOI: 10.5005/jihr-11055-0033 | Open Access | How to cite |
Abstract
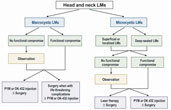
Vascular malformations of the head and neck represent a major subset of congenital vascular anomalies, with a marked predilection for the craniofacial region and frequent early-life presentation. These lesions, particularly venous and lymphatic types, exhibit progressive enlargement and may result in functional impairment, including compromised speech, mastication, swallowing, and airway patency, along with esthetic deformity. Their diffuse and infiltrative nature limits the predictability of surgical excision and increases the risk of recurrence and morbidity. Sclerotherapy has emerged as a minimally invasive modality that induces endothelial damage, thrombosis, and fibrosis, leading to a reduction in lesion volume. The aim of this review is to evaluate the role of sclerotherapy in the management of head and neck vascular malformations, focusing on epidemiology, lesion characteristics, sclerosant mechanisms, clinical outcomes, and complications. Evidence indicates that sclerotherapy is particularly effective in low-flow lesions, with improved functional and esthetic outcomes when applied with appropriate technique. In conclusion, sclerotherapy represents a reliable and effective modality in oral and maxillofacial practice, offering predictable outcomes with careful case selection and individualized treatment planning.
[Year:2026] [Month:January-June] [Volume:3] [Number:1] [Pages:5] [Pages No:45 - 49]
Keywords: Adhesive restorations, Case report, Conservative approach, Endocrown, Endodontically treated posterior teeth, Extensive coronal loss
DOI: 10.5005/jihr-11055-0027 | Open Access | How to cite |
Abstract
Endocrowns represent a conservative restorative approach for endodontically treated posterior teeth with extensive coronal loss. By utilizing the pulp chamber for macromechanical retention and adhesive cementation, endocrowns eliminate the need for post placement while preserving remaining tooth structure. This report describes two clinical cases of endodontically treated posterior teeth restored with adhesively bonded lithium disilicate endocrowns and followed for 6 months. Teeth with significant coronal destruction were restored using adhesively bonded endocrowns following standardized preparation and cementation protocols. Clinical and radiographic evaluations were performed to assess marginal integrity, retention, occlusion, and biological response during the follow-up period. Periapical radiographs were used to assess the quality of the root canal filling, periapical status, and the presence of secondary caries or marginal discrepancies. All restorations demonstrated satisfactory functional and esthetic outcomes, with no evidence of debonding, fracture, or secondary caries during the 6-month follow-up. Within the limitations of a short observation period and two cases, the findings of this report support the use of endocrowns as a conservative restorative option for posterior teeth following endodontic treatment.
[Year:2026] [Month:January-June] [Volume:3] [Number:1] [Pages:4] [Pages No:50 - 53]
Keywords: Case report, Complete denture, Complete denture prosthodontics, Denture stability, Neutral zone, Neutral zone recording, Resorbed ridge
DOI: 10.5005/jihr-11055-0032 | Open Access | How to cite |
Abstract
Aim and background: To describe a modified clinical technique using inverted U-shaped acrylic stoppers to stabilize neutral zone recording material and maintain the established vertical dimension during complete denture fabrication in patients with severely resorbed ridges. Technique: An accurately adapted mandibular record base was fabricated using autopolymerizing acrylic resin. Inverted U-shaped acrylic stoppers were incorporated onto the mandibular record base to function as vertical stops during neutral zone recording. Moldable neutral zone recording material was adapted around the acrylic stoppers, and functional movements were performed intraorally to dynamically mold the material. The stabilized neutral zone record obtained was used for tooth arrangement and contouring of polished denture surfaces. Conclusion: The incorporation of inverted U-shaped acrylic stoppers provides a simple, stable, and clinically effective method for neutral zone recording in complete denture fabrication. This modification improves stabilization of the recording material, maintains the vertical dimension during functional movements, and enhances the accuracy and reproducibility of the neutral zone record. Clinical significance: The use of inverted U-shaped acrylic stoppers during neutral zone recording improves stabilization of the recording material and preserves the vertical dimension, thereby enhancing denture stability, retention, function, and patient comfort, particularly in patients with severely resorbed mandibular ridges.


© 2026. Jaypee Brothers Medical Publishers (P) Ltd. | All Rights Reserved.


